

 Comparing Lisinopril with Other Ace Inhibitors
Mechanism and Action: How Lisinopril Stands Apart
I often imagine lisinopril as a quiet locksmith in the bloodstream, blocking ACE with precise patience. By preventing angiotensin I conversion it eases vascular tone and lowers afterload, helping hearts breathe better and improving perfusion.
Unlike many peers, lisinopril is active after oral absorption rather than needing hepatic activation; its hydrophilic profile and predominant renal excretion shape dosing decisions and distinct pharmacokinetics that prescribers weigh carefully in daily practice regularly.
By reducing angiotensin II, lisinopril diminishes aldosterone release, reduces sodium retention, and promotes vasodilation. Over time these shifts modulate remodeling and can improve morbidity signals seen in heart failure and postinfarction care across patient groups.
The drug also increases bradykinin, which can cause cough or angioedema; Occassionally this side effect ends therapy. Choosing lisinopril is thus a nuanced decision balancing efficacy, tolerability, and individual renal considerations in everyday clinical practice.
Comparative Effectiveness: Blood Pressure Control and Outcomes
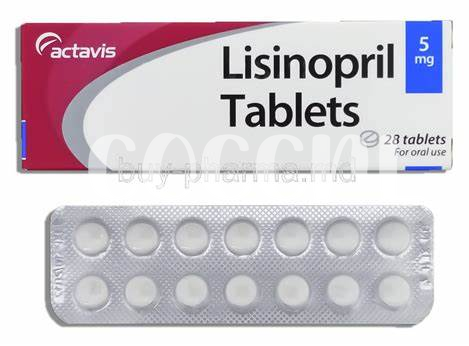
Clinicians often reach for lisinopril because trials show durable systolic and diastolic reductions comparable to other ACE inhibitors, with outcome benefits in heart failure and post‑MI populations across diverse cohorts and settings.
Population heterogeneity matters: response varies with age, race, and comorbidities, and some studies suggest marginal differences in albuminuria reduction or kidney disease progression between agents.
In practice, choice hinges on tolerability, dosing convenience, and cost. Occassionally adverse effects like cough or angioedema prompt a switch, so individualized prescribing balances real-world adherence with proven reductions in mortality and hospitalisation.
Side Effect Profiles: Cough, Angioedema, and Tolerability
Many patients report a dry cough with lisinopril, an effect linked to bradykinin; doctors discuss alternatives when it becomes troublesome and intolerable.
Rare but serious angioedema has Occured with lisinopril and other ACE inhibitors; emergency airway protection and rapid treatment are essential for survival.
Tolerability varies: lisinopril is generally well tolerated, yet dizziness, hyperkalemia, or renal function changes require monitoring and dose adjustments promptly in clinical practice.
Shared decision making helps balance benefits and adverse events; patients should be informed on warning signs, follow-up labs, and when to Recieve help.
Drug Interactions and Contraindications: Practical Prescribing Tips
When I first switched a patient to lisinopril, the conversation focused on simple checklists: confirm pregnancy status, review potassium supplements, and NSAID use. Emphasize that ACE inhibitors raise potassium and can worsen renal function in bilateral renal artery stenosis.
Watch for interactions with potassium sparing diuretics such as spironolactone or potassium chloride, and avoid concurrent use with aliskiren in diabetes. Lithium levels may increase; monitor. NSAIDs can blunt antihypertensive effects and increase renal risk.
Start low in renal impairment and titrate while monitoring creatinine and potassium at one to two weeks. Advise women of childbearing age to use effective contraception because ACE inhibitors are teratogenic. Occassionally switch to an ARB if cough or angioedema develops.
Dosing, Half-life, and Renal Adjustment Considerations
Lisinopril is typically given once daily, a simple regimen that supports adherence. Its oral bioavailability and an approximate half‑life of about 12 hours mean steady state is reached within a few days, so clinicians often titrate by doubling or halving doses at intervals to reach goal blood pressure. Teh predictable pharmacokinetic profile contrasts with prodrugs that require hepatic activation, making lisinopril a straightforward choice for many patients.
| Dose | Renal adjust |
|---|---|
| 5-40 mg daily | Reduce by 50% if CrCl <30 mL/min CKD |
Because lisinopril is excreted largely unchanged by the kidney, dose reductions or extended intervals are needed in renal impairment; begin with lower doses and monitor creatinine and potassium. In advanced CKD clinicians titrate slowly and may hold therapy if renal function acutely worsens. Occassionally patients require once‑every‑other‑day dosing. Practical steps: document baseline renal function and review concurrent potassium‑raising drugs.
Cost, Availability, and Real-world Adherence Patterns
Affordable generics make lisinopril a common first-line choice, lowering financial barriers and supporting steady therapy, which lowers risk of interruption for many patients.
Clinicians note occasional supply variability across regions, yet widespread formularies usually ensure ready access for most patients, aided by e-prescribing and pharmacies.
Adherence rises when dosing aligns with routines: once-daily schedules, clear titration plans, simple follow-up, and convenient refill programs sustain continuity for regular use.
Definately, pairing monitoring with patient education, prompt side-effect management, reminders, and copay assistance boosts persistence and long-term outcomes in diverse clinical settings. MedlinePlus: Lisinopril PubMed: Lisinopril